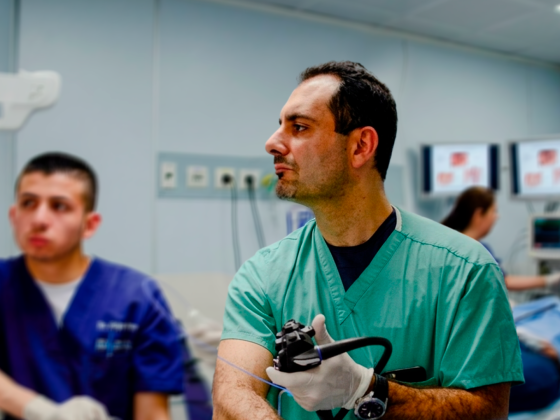
Medicine has long accepted a structural inefficiency that would be intolerable in almost any other field: the gap between finding a problem and fixing it. A scan picks something up. A biopsy confirms it. Then comes the referral, the scheduling, the wait, and often a second or third procedure performed by a different specialty in a different room on a different day. Each handoff carries risk, cost, and clinical deterioration, and for the sickest patients, the ones with unresectable cancer or malignant obstruction, that interval is not an administrative detail. It is the difference between a patient who is treated and a patient who is still waiting. Dr. Michel Kahaleh, who leads operations as Chief Executive Officer of Fight, argues that therapeutic endosonography is collapsing that gap, and that the consequences run far beyond the endoscopy suite. “The wait to diagnosis was never part of the therapy,” he says. “It was simply the distance between the instrument that could see and the one that could act. That distance is closing.”
Sampling Has Become Draining
For most of its history, endosonography was a diagnostic instrument and nothing more. It found the fluid collection, characterized it, sampled it, and then the clinical machinery took over: a second procedure was booked, a different team was engaged, and the patient went home to wait. The technology could see with remarkable precision but had no mandate to intervene. That division of labor was never a clinical judgment. It was a limitation of the tools, and the entire referral architecture of hospitals was built around accommodating it.
Kahaleh’s point is that the limitation is gone, and the architecture has not caught up. “Now we can sample and drain during the same session,” he says. For patients with unresectable cancer and complex gallbladder disease, that means cholecystitis can be confirmed and the gallbladder drained in a single sitting. “A patient who comes in for an answer can leave treated,” he says, without being routed to percutaneous drainage. Consider who that patient typically is: often frail, often oncologic, often poorly equipped to absorb a second anesthetic or another week of untreated infection. Eliminating the second procedure is not a convenience upgrade. It removes an entire category of exposure from the most vulnerable patients on the ward.
Diagnosis Has Become More Precise And More Capable
Acting faster is only defensible if the diagnosis holding up the decision is sound. This is where the argument becomes clinically serious rather than merely operational. Fine-needle aspiration and fine-needle biopsy allow tissue to be taken directly and assessed by pathology on site, which means staging and confirmation happen inside the procedure rather than days after it. “We stage a lesion and confirm the diagnosis right there,” Kahaleh says. “So we act on confirmed pathology.”
That phrase carries the weight of the whole case. The traditional sequence protected patients by forcing a pause between suspicion and intervention, with the pathology report serving as the checkpoint. Speed, in that model, meant acting on less information. On-site pathology evaluation dissolves the tradeoff: the checkpoint moves into the room instead of disappearing. The clinician is not intervening on a reasonable guess but on a confirmed result, in the same session. For hospital leadership weighing whether to invest in these capabilities, the distinction matters enormously. This is not a workflow shortcut that trades rigor for turnaround time. It is a reordering of where rigor sits in the sequence.
One Session Can Do The Work Of Several Departments
The most disruptive implication is institutional. Kahaleh describes a pancreatic neuroendocrine tumor that can be found, diagnosed, and ablated with the same instrument in the same session. In the liver, clinicians can visualize, biopsy, and measure portal pressure entirely from the inside, which is work that, as he puts it, “once belonged to interventional radiology.” For patients with malignant bowel obstruction, a gastroenteric anastomosis can deliver relief in the same session that identified the problem, sparing debilitated patients a complex surgery they may not survive well.
Read that list carefully and what emerges is not a new procedure but a redistribution of clinical territory. Capability that was previously spread across interventional radiology, surgery, and gastroenterology is converging into one instrument and one session. Health systems have organized budgets, staffing models, referral patterns, and capital planning around the old divisions. Those divisions are now technical history rather than clinical necessity, and the systems that recognize it first will treat patients sooner while carrying less procedural overhead. The ones that do not will keep paying for a sequence of handoffs the technology no longer requires. Kahaleh frames the outcome plainly: patients are getting care sooner and faster. The harder question, and the one administrators should be asking now, is whether their institutions are still structured to deliver it that way.
Follow Dr. Michel Kahaleh on LinkedIn for more insights on therapeutic endoscopy and therapeutic endosonography.